viernes, octubre 23, 2026
More
    Inicio Blog Página 7

    REIMAGINING ORPHAN DRUG ACCESS: INTEGRATING TECHNOLOGY INTO OUTCOME-BASED PAYMENT MODELS IN SPAIN

    Fernando Abdalla, Mathilde Daheron and Eloy Vicente

    Health Affairs & Policy Research, Weber Health Economics & Market Access, Weber Data & Technology, Weber

    INTRODUCTION

    Healthcare systems across Europe are increasingly turning to value-based healthcare models as a strategic framework to improve patient outcomes within the constraints of finite resources. Although promising in concept, the implementation of such models presents challenges in the context of complex, longterm conditions such as rare diseases. These conditions often involve diagnostic uncertainty, fragmented care pathways, and a lack of standardized metrics to assess health outcomes

    and service quality. This complexity complicates the assessment of the true value delivered to patients, particularly in multidisciplinary envi- ronments where care spans multiple levels of the health system1,2.

    Rare diseases, by their very nature, affect small patient populations, which makes traditional clinical trials difficult to conduct and limits the availability of robust evidence
    on safety, efficacy, and long-term benefit. For these reasons, orphan drugs—therapies developed specifically to treat rare conditions— tend to carry a higher degree of
    uncertainty at the time of market access. As a result, they often pose significant challenges for health authorities tasked with making reimbursement decisions based on incomplete data. The economic impact of these treatments is also considerable, as many orphan
    drugs are associated with very high costs per patient, placing additional pressure on already strained healthcare budgets3-7.

    Traditionally, pricing and reimbursement decisions for orphan drugs have relied on setting maximum prices based on expected therapeutic benefit, target population, and novelty, among other factors. However, in recent years, payers and manufacturers have sought
    more adaptive and risk-mitigating approaches. The absence of «perfect information»—particularly in terms of long-term clinical outcomes and real-world effectiveness—
    has driven interest in outcome-based payment (OBP) models. These agreements aim to link payment to actual health outcomes or financial performance, offering a more
    dynamic and evidence-informed pathway to reimbursement. This is especially relevant for high cost treatments where traditional cost-effectiveness frameworks may not be adequate to capture value8,9.

    In this context, technology is emerging as a critical enabler of OBP models, offering tools to
    design, implement, and monitor these agreements with greater transparency and precision. From real-world data platforms to artificial intelligence and digital registries, technological innovation is helping to reduce uncertainty, support outcome measurement, and facilitate coordination between stakeholders. The objective of this article is to analyze how technological solutions are being applied to the design, implementation, and monitoring of OBP agreements for orphan drugs and advanced therapies, highlighting their role in improving transparency, efficiency, and sustainability in drug financing.

    To this end, the article will begin with a theoretical overview of shared risk and outcome-based models, followed by an analysis of current OBP agreements internationally.
    It will then focus in detail on real-world examples of where technology has played a central role, before discussing the challenges and opportunities in this area, and concluding with recommendations for healthcare systems.

    THEORETICAL FRAMEWORK: SHARED RISK AGREEMENTS AND OUTCOME-BASED
    PAYMENTS

    Definitions

    Shared Risk Agreements (SRAs) and OBP models have emerged as pivotal contractual frameworks that distribute financial and clinical uncertainties between payers and
    pharmaceutical manufacturers. While these terms are often used interchangeably, they encapsulate nuanced differences. SRAs encompass a broader spectrum of arrangements, including those based on both financial and clinical performance outcomes. OBP models, a subset of SRAs, specifically refer to agreements where the final payment is explicitly tied to the achievement of predefined health outcomes in real-world clinical settings10.

    The essence of these models could be encapsuled by the following definition:

    OBP Agreements are structured reimbursement contracts between healthcare payers and pharmaceutical manufacturers that condition all or part of the financial transaction on the achievement of clinical or health system outcomes, with the objective of reducing uncertainty, improving accountability, and aligning value delivery with actual patient benefit11.

    OBP models differ from traditional pricing approaches by incor- porating real-world performance metrics into reimbursement structures. Under these models, a treatment’s effectiveness is monitored within a defined patient group over a specific timeframe, and future reimbursement is tied to the clinical and economic outcomes achieved. OBPs are designed to meet the growing need for transparency, flexibility, and evidence-based decisions particularly as many high-cost treatments, like orphan drugs, are launched with limited long-term data on their efficacy10.

    Types of Agreements

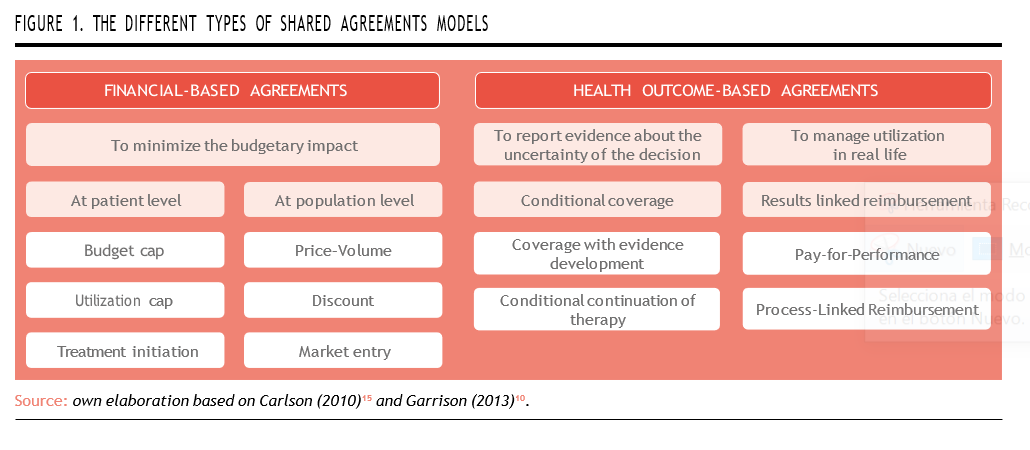
    Outcome-based models can be broadly categorized into two primary groups, based on the nature of uncertainty they aim to mitigate, and the metrics employed to define success.

    Financial-Based Agreements

    These agreements primarily focus on minimizing the budgetary impact and ensuring cost containment when adopting new, often expensive therapies. The outcomes measured are financial rather than clinical, aiming to make expenditures more predictable.

    Key types of financial-based agree- ments include12:

    • Price-Volume Agreements: These link the price of a drug to the volume purchased. As volume increases, the unit price may decrease, thus mitigating excessive financial exposure due to overuse.
    • Discount Schemes and Rebates: These arrangements offer fixed or tiered price reductions, ensuring affordability without evaluating clinical outcomes.
    • Budget/Utilization Caps: These set a maximum cumulative expenditure or dose level. Costs beyond the agreed limit are absorbed by the manufacturer.
    • Treatment Initiation Agreements: The manufacturer covers initial treatment cycles until sufficient data justifies full reimbursement.
    • Market Entry Agreements: Temporary price reductions are offered to accelerate market uptake, often in exchange for faster access or wider patient inclusion.

    While effective in stabilizing financial risk, these models do not directly incentivize real-world clinical performance or health system efficiency. They are generally easier to implement but less aligned with VBHC principles.

    Health Outcome-Based Agreements

    These models represent the core of OBP strategies and are designed to link reimbursement to actual clinical outcomes experienced by patients in real-world settings. They address clinical uncertainty, which is particularly pronounced in the case of orphan drugs due to limited trial populations and short study durations.

    Key types of health outcome-based agreements include12:

    • Pay-for-Performance: The most emblematic model of OBP, these agreements stipulate that payment is contingent on achieving specific clinical For instance, reimbursement may depend on a drug achieving survival, disease remission, or biomarker targets. If the drug fails to meet those thresholds, the manufacturer must provide rebates, discounts, or reimburse the cost. Their success depends on having robust outcome metrics, consistent patient monitoring, and a data infrastructure that supports longitudinal analysis.
    • Conditional Continuation of Therapy: Under these models, the continuation of coverage for a given patient is based on short term response milestones. Only those who demonstrate early benefit are allowed to continue This minimizes unnecessary spending and ensures clinical appropriateness at the individual level.Coverage with Evidence Development: Reimbursement is granted conditionally, requiring the manufacturer to collect additional real-world evidence (RWE) post- This may involve observational studies, registries, or ongoing trials. This model provides earlier access while reducing long-term risk, and it’s often used in situations with accelerated regulatory approvals.
    • Process-Linked Reimbursement: These less common agreements reimburse a product based on its impact on the broader care pathway. For example, a diagnostic test might be reimbursed based on its ability to reduce downstream treatments or hospital While more typical for medical devices, this logic can be applied to stratification tools used with high-cost drugs.

    In the context of orphan drugs, health outcome-based agreements are especially pertinent due to the unique characteristics of these treatments8,13:

    • High cost and limited patient populations make cost-effectiveness highly variable across individuals.
    • A high degree of clinical uncertainty—stemming from small clinical trials, heterogeneous responses, and limited generalizability of results— which makes evidence-based decision-making more difficult.
    • Lack of long-term data at market entry increases risk for payers.
    • Need for early access compels regulators and health systems to approve reimbursement based on limited evidence.

    By linking reimbursement to patient results, OBP models offer a pragmatic path to access while ensuring ongoing evaluation. However, they are also more demanding: they require data capture infrastructure and increased administrative burden, welldefined outcomes, collaboration across stakeholders, and often third-party validation (Figure 1)14.
    CURRENT LANDSCAPE OF OUTCOME-BASED PAYMENT AGREEMENTS: GLOBAL PERSPECTIVES

    Before exploring concrete examples of technological integration into OBP models, it is essential to examine the current landscape of OBP agreements globally. This provides contextual understanding of where such agreements are most prevalent, and what types are being adopted.

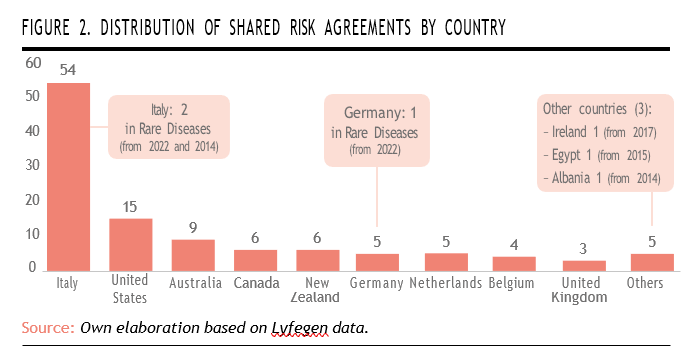
    The following descriptive analysis is based on a database compiled by Lyfegen16, a company that collaborates with the Weber Foundation, publishers of newsRARE magazine. The dataset includes publicly available information on 153 OBP agreements implemented between 2008 and December 2023 (up to December 2022 in the case of Spain). Of these, 41 agreements were concluded in Spain (excluded from the current analysis), while the remaining 112 were executed across fourteen other countries. The agreements vary in nature, encompassing both financial-based and clinical outcome-based models.

    According to the analyzed data, Italy leads with the highest number of OBP agreements globally, totaling 54. It is followed by the United States (15 agreements), Australia (9), and New Zealand (6). This distribution illustrates that OBP models have been adopted across a diverse set of countries, regardless of population size or the structural characteristics of their healthcare systems.

    When focusing specifically on rare diseases, the data reveals a more limited adoption of OBP agreements across select countries. Italy stands out as the most active, having implemented two agree- ments related to rare diseases, one in 2022 and another in 2014; howe- ver, these represented only 4% of the total OBP agreements imple- mented in the country during the period. Germany follows with one rare disease agreement initiated in 2022. Among the group of «other countries,» three nations have each introduced a rare disease-focused OBP agreement: Ireland (2017), Egypt (2015), and Albania (2014). While these numbers are modest relative to total OBP activity, they highlight growing international willingness to apply performance-based approaches in the high-uncertainty context of rare disease treatments (Figure 2).
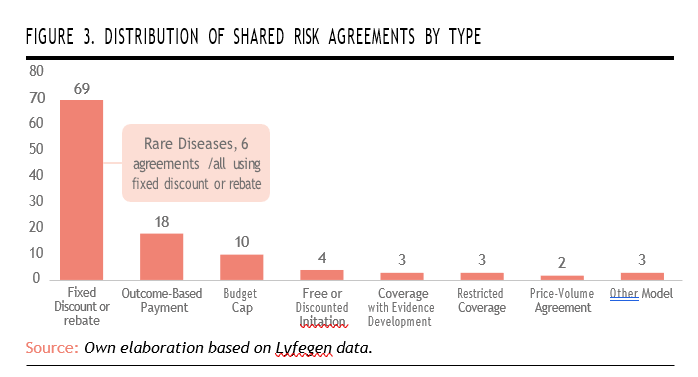
    The analysis also reveals a clear predominance of financial-based agreements (such as fixed discount or rebate schemes), totaling 69 agreements, which represents 62% of the total. OBP agreements rank second, with 18 agreements.

    When it comes to rare diseases, the data shows that these conditions remain underrepresented within outcome-based frameworks. All of the agreements in rare diseases relied exclusively on fixed discount or rebate models. This suggests that while rare diseases are starting to be included in risk-sharing schemes, they are still largely managed through simpler, financially-oriented mechanisms. The absence of outcome-based models in this category highlights a missed opportunity to better align reimbursement with clinical benefit, particularly given the high uncertainty and cost associated with orphan drugs. It also points to the continued need for robust data infrastructure and outcome measurement tools tailored to rare disease contexts (Figure 3).
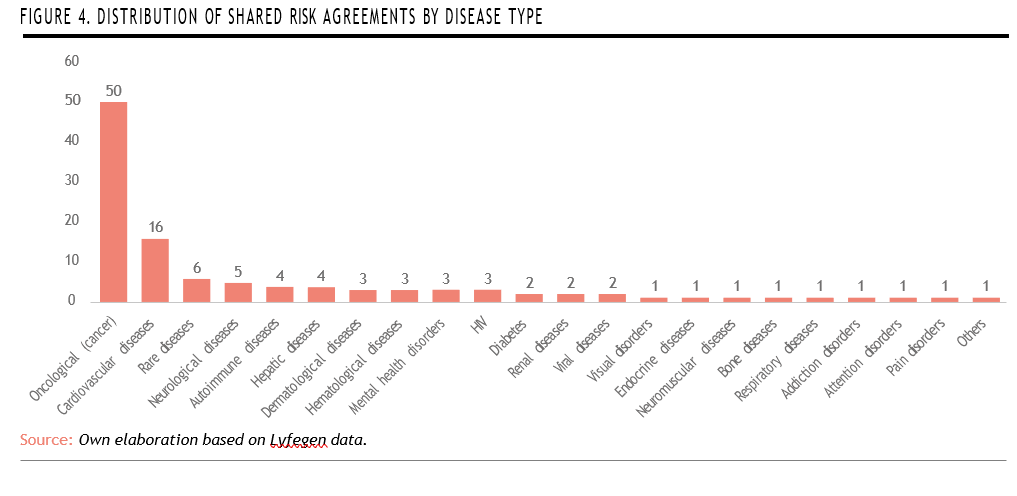
    A disease-specific analysis reveals a strong concentration of shared risk agreements in severe or chronic conditions, with oncological diseases (cancer) leading by a significant margin (50 agreements, representing 45% of the total), followed by cardiovascular diseases with 16 agreements. Rare diseases rank third, with 6 agreements, indicating a growing—though still limited— interest in applying innovative payment models to this highly complex therapeutic area.

    Despite their relatively high placement, the number of agreements for rare diseases remains modest compared to their clinical relevance and economic impact, suggesting room for further expansion of outcome-based and risksharing strategies in this domain (Figure 4).
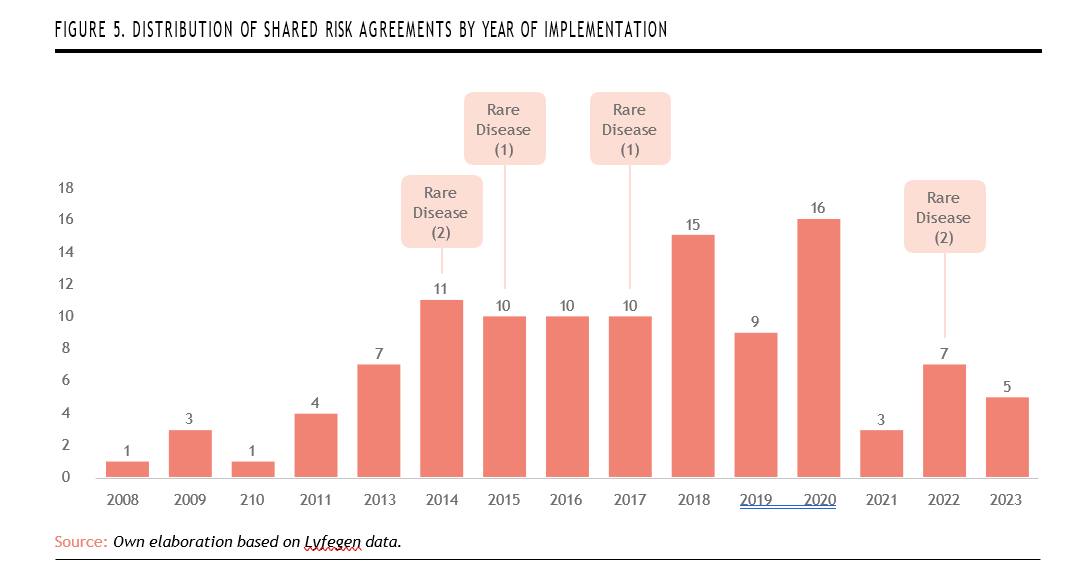
    A higher frequency of agreements is also observed starting from 2013,reaching a peak in 2020 with 16 agreements. Rare diseases appear sporadically throughout the implementation timeline. The first recorded rare disease agreements emerged in 2014 with two agreements, followed by one agreement each in 2015 and 2017. The most recent activity occurred in 2022, with another two agreements. This distribution suggests a cautious but sustained inclusion of rare diseases within shared risk frameworks. However, their intermittent presence also reflects ongoing challenges in integrating complex, high-uncertainty therapies into structured outcome-based models on a consistent basis (Figure 5).
     

    TECHNOLOGICAL INTEGRATION IN OBP AGREEMENTS

    As healthcare systems continue to evolve in the digital age, the integration of smart technologies into OBp models is becoming increasingly common—and necessary. Tools such as artificial intelligence, electronic health records, and automated platforms are transforming how treatments are assessed and reimbursed, making it possible to link payments directly to real-world clinical outcomes. This shift not only enhances the feasibility of performance-based models but also raises expectations for greater accountability and transparency in healthcare financing.

    In the following section, we will examine how specific technologies are being applied to OBP models, focusing on practical examples that illustrate their role in streamlining implementation, improving data collection, and supporting evidence-based decision-making.

    Valtermed

    Valtermed is a centralized digital platform developed by the Spanish National Health System to assess the real-world effectiveness of pharmaceutical treatments. Its main purpose is to collect and analyze patient outcomes from the use of new and often high-cost medicines, helping improve treatment safety and effectiveness while supporting decisions related to value-based reimbursement and resource allocation.

    The system gathers detailed patient-level data—covering clincal, therapeutic, and administrative aspects—which allows healthcare providers to monitor each patient’s condition from the beginning of treatment and track their progress over time. The data collected are guided by pharmaco-clinical protocols, which are created through collaboration among expert working groups recognized by national healthcare authorities18.

    Data entry is carried out by health- care professionals through a secure, web-based tool that is connected to regional health information systems. This integration ensures that information is consistently recorded and shared across the public health- care network17,18.

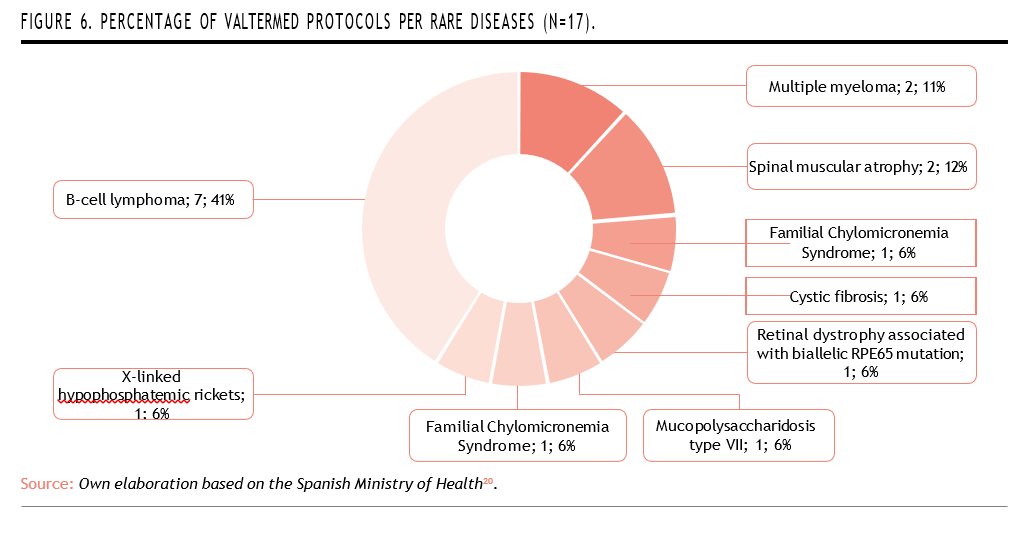
    Valtermed plays an especially important role in the field of rare diseases, where reliable data are often scarce19. Out of the 21 active protocols currently in place within the system, 17 focus specifically on rare disease treatments, reinforcing its value in generating real-world evidence for complex, low-prevalence conditions (Figure 6)20.
    One of the first structured examples of a technology-enabled OBP model in Spain is the case of Luxturna. This agreement illustrates that it is possible to tie drug reimbursement directly to clinical outcomes— even in the context of rare diseases where uncertainty is high. It also sets a precedent for future models by using the Valtermed platform as the central tool for monitoring and validating patient results21.

    Voretigene neparvovec (Luxturna) is a gene therapy developed to treat both children and adults with vision loss caused by a hereditary retinal dystrophy linked to biallelic mutations in the RPE65 gene, provided that patients have enough viable retinal cells to benefit from the therapy22.

    Through Valtermed, clinical out comes for patients receiving Luxturna are tracked across hospitals within the Spanish National Health System. Payment to the manufacturer (Novartis) is conditional on the patient showing measurable improvements in visual function at specific time points—such as 30, 90, and 365 days after treatment. If these predefined clinical goals are not achieved, a portion of the treatment cost must be reimbursed by the manufacturer23.

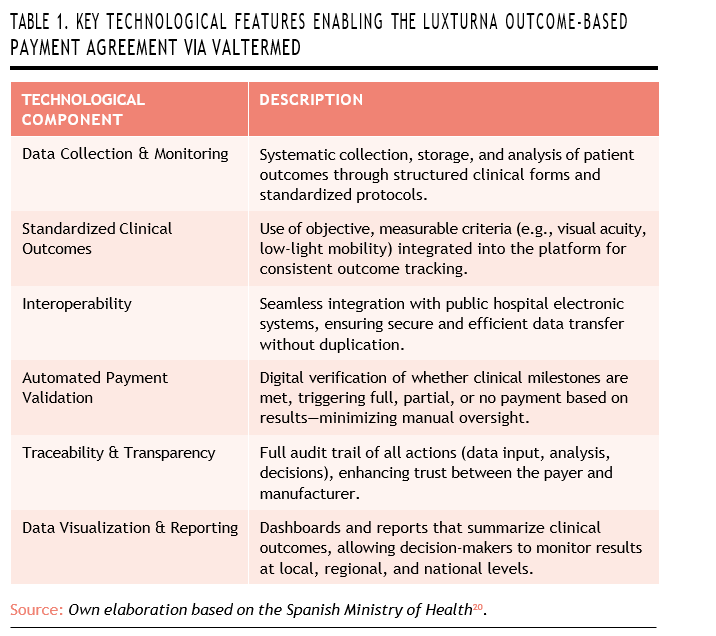
    Several technological components made the Luxturna OBP agreement possible, with the Valtermed plat- form at its core. Valtermed enables the systematic collection, storage, and analysis of patient outcomes for high-impact therapies. It relies on structured clinical forms, standardized measurement protocols, and long-term patient monitoring to ensure consistency and reliability in data gathering.

    A key feature of the agreement is the standardization of clinical outcomes. To make the contract verifiable, objective and measura- ble criteria—such as visual acuity tests or assessments of mobility in low-light conditions—were clearly defined. These outcomes are fully integrated into the digital platform, allowing for automated comparisons and centralized reporting across different hospitals.

    Valtermed is also designed to work seamlessly with the electronic systems used in public hospitals. This interoperability ensures that clinical data can be securely transferred without duplicating records or disrupting existing workflows, making the process more efficient for healthcare professionals.

    Another important element is the automatic validation of payment milestones. The platform determi- nes whether the clinical outcomes specified in the agreement have been met, and based on this, it triggers either full reimbursement, partial payment, or a refund. This process is fully embedded within the digital workflow, reducing administrative workload and minimizing room for subjective interpretation.

    In addition, the platform provides full traceability and transparency. Every step—from data entry to outcome analysis and payment decisions—is digitally recorded and auditable. This transparency strengthens trust between the healthcare payer (Spain’s National Health System) and the manufacturer (Novartis).

    Finally, Valtermed offers powerful tools for analysis and visualization. It produces dashboards and summary reports for decision-makers at both regional and national levels, making it easier to track the progress of clinical outcomes over time and across institutions (Table 1).
    Lyfegen

     Founded in 2018 and based in Basel, Switzerland, Lyfegen16 is a health technology company focused on transforming how healthcare systems manage the cost and value of inno- vative treatments. Its main product, the Lyfegen Drug Contracting Simu- lator, is currently used in more than 40 countries by insurers, hospitals, and pharmaceutical companies. The platform supports the design and management of value-based reimbursement agreements by allowing users to simulate various pricing models, including outcome-based and performance-based contracts. Through this tool, both payers and manufacturers can evaluate the financial and clinical impact of therapies and negotiate agreements more efficiently and transparently24.

    The Lyfegen platform offers several key features that support more agile and evidence-informed negotiations. It enables real-time financial simulations across a variety of scenarios, incorporating variables such as price, treatment volume, patient adherence, taxes, and more. Users can automatically generate com- parative business cases—such as best-case, base-case, and worst-case scenarios—which help guide strategic decisions and improve the quality of negotiations. The platform also provides a secure and collaborative digital workspace, allowing both global and local teams to work together with full version control and access permissions. Its focus on innovative reimbursement models—ranging from value- and outcome-based pricing to installment plans and performance guarantees—makes it especially well-suited for high-cost and complex therapies like gene therapies and rare diseases. According to the company, Lyfegen can reduce negotiation times by up to 18%, significantly cutting down on manual calculations and administrative workload (Figure 7)24.
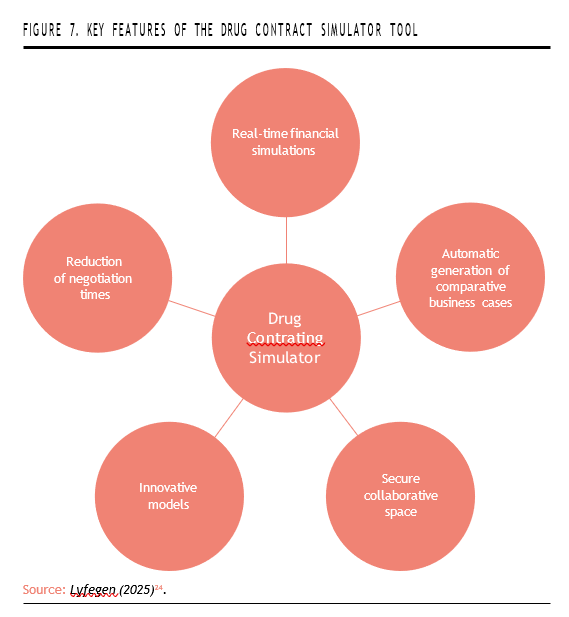
    Overall, the Lyfegen platform streamlines the negotiation process by making it more agile, transparent, and data-driven. It reduces reliance on complex manual calculations, supports smooth collaboration among international teams, and speeds up decision-making through access to a rich library of real-world agreements and reference models. This combination of features allows stakeholders to compare options quickly and accu- rately assess the financial impact of each proposed contract, ultimately leading to more effective and informed agreements.

    Technological Components of the Platform

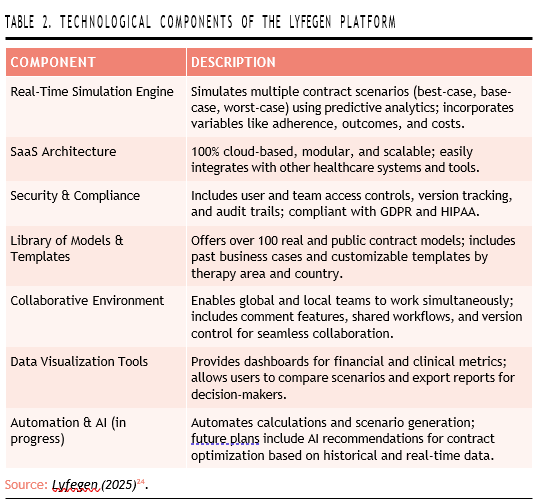
    The Lyfegen platform is built around a set of advanced technological components that enable flexible, data-rich contracting. At its core is a realtime simulation engine that can automatically calculate multiple contract scenarios using financial algorithms and predictive analytics. These simulations take into account a wide range of variables, including patient adherence, treatment duration, taxes, clinical outcomes (in the case of outcome-based models), and cost-effectiveness thresholds24.

    As a fully cloud-based software-as-a-service (SaaS) platform, Lyfegen is accessible from anywhere and offers a modular, scalable design that allows for easy integration with other digital tools in the healthcare ecosystem.

    Security is another critical component: the platform includes user-level access control, team- and project-based permissions, full version tracking, and audit trails. It is also designed to comply with major data protection regulations such as GDPR and HIPAA24.

    To support contract customization and benchmarking, Lyfegen provides access to a rich library of over 100 real-world and public contract models. These include historical business cases and customizable templates tailored to different therapies and national contexts. Collaboration is also central to the platform’s functionality: teams across geographies can work together simultaneously within the platform, communicate through built-in comment and review features, and follow a shared digital workflow for approvals and negotiations24.

    Interactive data visualization tools are embedded into the system to support decision-making. Users can access dynamic dashboards showing the financial impact and outcome metrics of different the- rapies, compare scenarios directly, and export reports for presentation to internal or external committees24.

    Finally, automation is a growing part of the platform’s development roadmap. Many tasks—such as scenario generation and financial calculations—are already automated, and the company is exploring the integration of artificial intelligence to recommend optimal contract models based on historical data and current negotiation parameters (Table 2)24.
    mHealth apps

    The use of mobile health applications (mHealth apps) has grown rapidly in recent years, with more than 350,000 apps currently available on the market25. These digital tools offer a broad range of functions that can significantly enhance patient care, particularly by allowing healthcare professionals to access clinical data in real time. Key features of these apps include symptom tracking, monito- ring of treatment outcomes, and the recording of medication adherence26. This ability to collect structured, time-sensitive patient data positions mHealth apps as promising tools to support OBP models.

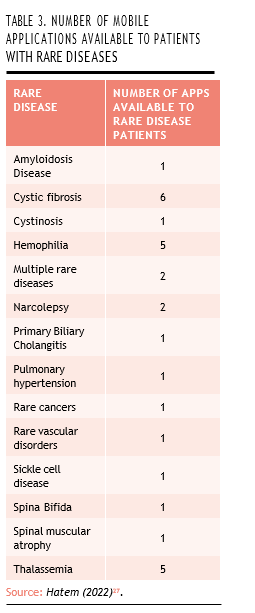
    Their potential is especially relevant in the context of rare diseases, where patient numbers are small and clinical follow-up can be highly individualized. Many patients with rare conditions already rely on mobile apps for disease management, offering a natural entry point for integrating these technologies into OBP frameworks. A study conducted by Hatem (2022) identified 29 mobile applications specifically designed for 14 rare diseases or disease groups. Among the most frequently addressed conditions were cystic fibrosis, hemophilia, and thalassemia, reflecting both the clinical need and the potential for digital innovation in these areas (Table 3)27.
    Some mobile health applications have been developed specifically for patients with rare diseases, offering tailored functionalities that support both self-management and clinical oversight. One example is the Fabry App28, designed for individuals living with Fabry disease—a rare, X-linked lysosomal storage disorder caused by mutations in the GLA gene. This genetic defect leads to a deficiency of the enzyme alpha-galactosidase A, resul- ting in the accumulation of a substan- ce called globotriaosylceramide (GL-3 or Gb3) in various tissues. Over time, this buildup can cause a wide range of complications, including neurological, kidney, heart, inner ear, and cerebrovascular problems29,30.

    The Fabry App provides patients with a user-friendly platform to log daily health information, including symptoms and medication intake. The data entered by the patient is securely transmitted to a password-protected online portal, where healthcare professionals can access and review the information. This continuous, remote monitoring helps clinicians track disease progression and adjust care more effectively, supporting the kind of real-world evidence collection that is crucial for OBP models28.

    Another notable example is Haemoassist®, a mobile application designed to support self-management for individuals with hemophilia. This digital tool allows patients to record treatment administrations, bleeding episodes, and other clinically relevant information in real time using an intuitive interface. By facilitating structured and timely data entry, the app helps improve adherence to therapy and enables more accurate clinical monitoring31-33.

    Haemoassist® is also linked to a web based portal, which aggregates patient-reported data and presents it through statistical sum- maries and visual dashboards. This setup allows healthcare profes- sionals to easily review trends and make infored treatment decisions based on real-world insights31-33.

    Given their functionality, mobile health applications offer valuable opportunities to support OBP models. Their ability to capture reliable, patient-level data makes them ideal tools for tracking clinical outcomes, and their integration into OBP frameworks could be strengthened through closer collaboration between payers and pharmaceutical companies.

    CHALLENGES AND OPPORTUNITIES IN IMPLEMENTING TECHNOLOGY IN OBP AGREEMENTS 

    Implementing OBP models, particularly in the context of rare diseases, demands a coordinated infrastruc- ture capable of capturing robust real world data, managing financial flows over time, and aligning stake- holder objectives. However, despite the promise of tools such as Valtermed, Lyfegen, and mHealth apps and several others, several technical, organizational, and regulatory challenges persist—alongside sig- nificant opportunities for innovation and improvement.

    Data Quality and Integration

    High-quality, interoperable data systems lie at the heart of OBP frameworks. Although Valtermed demonstrates interoperability with regional hospital systems, broader data integration remains limited. Fragmented electronic health records and inconsistent data standards across regions hinder comprehensive tracking of clinical outcomes. Additionally, registering longitudinal data in mHealth apps poses challenges in patient adherence and data completeness; inconsistent usage can generate incomplete datasets, undermining the reliability of performance-linked payments34.

    Administrative Burden

    OBP agreements impose significant administrative overhead, including data collection, outcome validation, and contractual reconciliation over time. As reported in studies of managed entry agreements for advanced therapies, these burdens can reduce feasibility and scalability35. The complexity is exacer- bated when spread over several years, requiring multiyear financial tracking often incompatible with existing 12-month healthcare budgeting cycles. The result is potential resistance from providers and payers faced with manual processes and contractual complexity.

    Payment Architecture and Financial Flows

    Traditional healthcare financing sys- tems are structured around upfront or lowest-cost budgeting; shifting to spread or outcome-adjusted pay- ments presents logistical hurdles. Governance questions arise around who purchases the therapy and how outcomes trigger payments—processes that must integrate clinical systems and financial ledgers in real time. To resolve this, newer models propose centralized payer procurement— rather than provider-led invoicing— with payers distributing treatment costs based on validated outcomes, similar to approaches taken with Lux- turna. However, this necessitates new governance frameworks and accounting adaptations35.

    Contractual and Governance Frameworks

    Achieving stakeholder alignment on outcomes, timelines, and termination triggers is a perennial challenge. Literature emphasizes the difficulty of reaching consensus on clinical endpoints, data collection processes, and optimal payment duration, especially in the context of high-cost rare-disease therapies. Additionally, explicit contracts must address potential adverse selection, where payers or manufacturers might influence patient inclusion based on expected outcomes. Multi-stakeholder governance structures—such as independent steering committees—are essential to maintain transparency and oversight.

    Regulatory and Legal Constraints

    OBP models must adhere to regulations governing data privacy, healthcare reimbursement, and accounting. The European GDPR restricts the use of individual patient data unless properly anonymized. Bud get cycle constraints and accrual accounting rules may treat installment payments differently from lumpsum purchases, complicating implementation at the national level. Harmonizing these frameworks across jurisdictions remains an ongoing challenge.

    Long-Term Agreements vs. Annual Budget Cycles

    One of the most pressing challenges in implementing OBP models is the misalignment between long term payment structures and the short term nature of hospital bud geting. Most public healthcare ins- titutions operate on annual budget cycles, which are not well suited to manage multi-year or outcome-de- pendent payments that may unfold over extended periods. This issue becomes even more complex in cases where clinical outcomes will only be available far into the future—for example, some gene or cell therapies require up to 12 years of follow-up to confirm their full the rapeutic value. In such cases, hos- pitals and payers face significant uncertainty about how to account for potential future liabilities, how to record these contracts on their financi al statements, and how to plan for reimbursement beyond the typical one-year horizon. Without specific legal or accounting mechanisms to address this temporal mismatch, long-term OBP contracts may encounter ins- titutional resistance or fail to scale effectively within existing public finance frameworks.

    Opportunities and Enablers

     Despite these challenges, techno- logical advances present numerous opportunities:

    • Automated, integrated data platforms—such as Valtermed and mHealth apps—can reduce manual workload, enhance data quality, and facilitate near real-time outcome tracking.
    • Centralized digital negotiation tools, exemplified by Lyfegen, can streamline agreement design, facilitate benchmarking using a global library of contracts, and reduce negotiation timelines.
    • Emerging payment models, such as outcome-linked annuity systems, spread financial risk and align incentives over time.
    • Governed registries and external audit structures can help build trust and compliance, offering visible oversight while addressing privacy and governance require-
    • Cross-country collaboration and standard-setting bodies can promote shared data standards, aligned endpoints, and streamlined implementation pathways.

    In conclusion, the integration of technology into OBP models represents a significant opportunity to improve access, transparency, and sustainability in the financing of orphan drugs. As demonstrated through the use of platforms such as Valtermed in Spain and Lyfegen internationally, digital tools are increasingly capable of addressing the uncertainty and complexity that often surround rare disease treatments. These technologies enable the systematic collection of real-world outcomes, support the design and monitoring of risk-sharing agreements, and enhance collaboration among stakeholders.

    However, this evolution is not without its challenges. Issues related to data interoperability, administrative burden, legal frameworks, and financial structures continue to limit the scalability of OBP models. Yet, as healthcare systems gain experience and invest in digital infrastructure, many of these barriers are becoming more manageable. Furthermore, the growing use of mobile health applications offers a promising frontier for patient engagement and long- term monitoring, especially in rare diseases where data is traditionally scarce.

    Ultimately, realizing the full poten- tial of OBP in rare diseases will require continued cross-sector collaboration, regulatory flexibility, and investment in scalable digital ecosystems. Technology is not the solution in itself, but it is a critical enabler of a more adaptive, patient-centered model of drug reimbursement.

    References

    1. Implementing Value-Based Health Care in Europe [Internet]. 2020. Available from: https://eithealth. eu/wp-content/uploads/2020/05/Implementing-Va- lue-Based-Healthcare-In-Europe_web-4.pdf
    2. Khalil H, Ameen M, Davies C, Liu C. Implementing value-ba- sed healthcare: a scoping review of key elements, outco- mes, and challenges for sustainable healthcare systems. Front Public Health. 2025;13:1514098.
    3. Freitag A, Iheanacho I. Rare Diseases and Orphan Drugs. Where are We Now? [Internet]. Available from: https:// www.evidera.com/wp-content/uploads/2020/10/A05_ RareDiseases_EFFall20.pdf
    4. Andreu P, Karam J, Child C, Chiesi G, Cioffi The Burden of Rare Diseases: An Economic Evaluation. 2022;
    5. Villa F, Di Filippo A, Pierantozzi A, Genazzani A, Addis A, Trifirò G, et al. Orphan Drug Prices and Epidemiology of Rare Diseases: A Cross-Sectional Study in Italy in the Years 2014–2019. Front Med [Internet]. 2022 [cited 2025 Jul 4];9. Available from: https://www.frontiersin.org/journals/ medicine/articles/10.3389/fmed.2022.820757/full
    6. Hanchard MS. Debates over orphan drug pricing: a meta-na- rrative literature Orphanet J Rare Dis. 2025;20(1):107.
    7. Pijeira Perez Y, Wood E, Hughes Costs of orphan me- dicinal products: longitudinal analysis of expenditure in Wales. Orphanet J Rare Dis. 2023;18:342.
    8. Facey KM, Espin J, Kent E, Link A, Nicod E, O’Leary A, et Implementing Outcomes-Based Managed Entry Agree- ments for Rare Disease Treatments: Nusinersen and Tisa- genlecleucel. PharmacoEconomics. 2021;39(9):1021–44.
    9. Langley PC. Formulary Submissions: Value Claims, Protocols and Outcomes Based Contracting in Rare Innov Pharm. 2022;13(3):10.24926/iip.v13i3.5020.
    10. Garrison LP, Towse A, Briggs A, de Pouvourville G, Grue- ger J, Mohr PE, et Performance-based risk-sharing arrangements-good practices for design, implementation, and evaluation: report of the ISPOR good practices for performance-based risk-sharing arrangements task force. Value Health J Int Soc Pharmacoeconomics Outcomes Res. 2013;16(5):703–19.
    11. Wenzl M, Chapman S. Performance-based managed entry agreements for new medicines in OECD countries and EU member states [Internet]. 2019 [cited 2025 Jun 3]. Avai- lable from: https://www.oecd.org/en/publications/ performance-based-managed-entry-agreements-for- new-medicines-in-oecd-countries-and-eu-member- states_6e5e4c0f-en.html
    1. Dévora C, Abdalla F, Zozaya Modelos de financiación en enfermedades raras: de donde venimos y hacia donde vamos. 2022 [cited 2025 Jun 3];7(2). Available from: https:// weber.org.es/wp-content/uploads/2022/10/nR-13- Vol-7-num-2-2022-WEB.pdf
    2. Gonçalves Value-based pricing for advanced therapy medicinal products: emerging affordability solutions. Eur J Health Econ. 2022;23(2):155–63.
    3. Bohm N, Bermingham S, Grimsey Jones F, Gonçalves-Brad- ley DC, Diamantopoulos A, Burton JR, et al. The Challenges of Outcomes-Based Contract Implementation for Medici- nes in Europe. Pharmacoeconomics. 2022;40(1):13–29.
    4. Carlson JJ, Sullivan SD, Garrison LP, Neumann PJ, Veenstra Linking payment to health outcomes: a taxonomy and examination of performance-based reimbursement sche- mes between healthcare payers and manufacturers. Health Policy Amst Neth. 2010;96(3):179–90.
    5. About Lyfegen | Innovating Healthcare Solutions [Internet]. 2025 [cited 2025 Jul 2]. Available from: https:// www.lyfegen.com/about-us
    6. Jørgensen J, Hanna E, Kefalas P. Outcomes-based reimbur- sement for gene therapies in practice: the experience of recently launched CAR-T cell therapies in major European countries. J Mark Access Health 2020;8(1):1715536.
    7. Ministerio de sanidad, consumo y bienestar social, Secretaría general de sanidad y consumo, Dirección general de cartera bàsica de servicios del SNS y farmacia. Preguntas y repuestas frecuentes sobre el sistema de información para determinar el valor terapéutico en la pràctica clínica real de los medica- mentos de alto impacto sanitario y econoómico en el sistema nacional de salud (Valtermed) [Internet]. 2019 [cited 2025 Jun 23]. Available from: https://www.sanidad.gob.es/areas/ farmacia/infoMedicamentos/valtermed/docs/VALTER- pdf
    8. Arganda C. EERR: Valtermed y riesgo compartido para re- ducir incertidumbres | @diariofarma [Internet]. diariofarma. 2019 [cited 2025 Jun 23]. Available from: https://diario- com/2019/02/13/eerr-valtermed-y-riesgo-com- partido-para-reducir-incertidumbres
    9. Ministerio de Ministerio de Sanidad – Áreas – VAL- TERMED: Resultados en salud [Internet]. [cited 2025 Jun 23]. Available from: https://www.sanidad.gob.es/areas/ farmacia/infoMedicamentos/valtermed/home.htm
    10. Ministry of Health. Pharmacoclinical Protocol For The Use Of Voretigene Neparvovec In The Treatment Of Retinal Dystrophy Due To Biallelic Rpe65 Mutation In The Natio- nal Health System [Internet]. 2021. Available from: https://

    www.sanidad.gob.es/areas/farmacia/infoMedicamen- tos/valtermed/docs/20210504_I_Protocolo_voreti- gen_neparvovec_distrofia_retiniana.pdf

    1. European Medices EPAR: Luxturna [Internet]. 2018 [cited 2025 Jun 25]. Available from: https://www.ema. europa.eu/en/medicines/human/EPAR/luxturna
    2. Iglesias-López C, Agustí A, Vallano A, Obach M. Financing and Reimbursement of Approved Advanced Therapies in Several European Countries. Value Health J Int Soc Pharma- coeconomics Outcomes Res. 2023;26(6):841–53.
    3. Pharmaceutical Simulation | Accelerate Negotia- tions with Lyfegen [Internet]. 2025 [cited 2025 Jul 2]. Availa- ble from: https://www.lyfegen.com/pharma/simulator
    4. Wells C, Spry C. An Overview of Smartphone Apps: CADTH Horizon Scan [Internet]. Ottawa (ON): Canadian Agency for Drugs and Technologies in Health; 2022 [cited 2025 Jul 2]. (CADTH Horizon Scans). Available from: http://www.ncbi. nih.gov/books/NBK595384/
    5. Collado-Borrell R, Escudero-Vilaplana V, Narrillos-Moraza Á, Villanueva-Bueno C, Herranz-Alonso A, Sanjurjo-Sáez
    6. Patient-reported outcomes and mobile applications. A review of their impact on patients’ health outcomes. Farm Hosp. 2022;46(3):173–81.
    7. Hatem S, Long JC, Best S, Fehlberg Z, Nic Giolla Easpaig B, Braithwaite Mobile Apps for People With Rare Diseases: Review and Quality Assessment Using Mobile App Rating Scale. J Med Internet Res. 2022;24(7):e36691.
    8. D’Amore S, Mckie M, Fahey A, Bleloch D, Grillo G, Hughes M, et al. Fabry App: the value of a portable tech-

    nology in recording day-to-day patient monitored infor- mation in patients with Fabry disease. Orphanet J Rare Dis. 2024;19:13.

    1. Germain Fabry disease. Orphanet J Rare Dis. 2010;5:30.
    2. Schiffmann R, Fuller M, Clarke LA, Aerts JMFG. Is it Fabry disease? Genet 2016;18(12):1181–5.
    3. Haemoassist | Pfizer España | Pfizer España [Internet]. [cited 2025 Jun 26]. Available from: https://www.pfizer.es/salud/ sitios-web-y-aplicaciones/haemoassist
    4. Redacción. Una aplicación facilita el seguimiento en he- mofilia [Internet]. Diario de Sevilla. 2015 [cited 2025 Jun 26]. Available from: https://www.diariodesevilla.es/ sociedad/aplicacion-facilita-seguimiento-hemofi- html
    5. Haemoassist, nueva app para los pacientes con hemofilia [Internet]. COCEMFE. 2015 [cited 2025 Jun 26]. Available from: https://www.cocemfe.es/informa- te/noticias/haemoassist-nueva-app-para-los-pacien- tes-con-hemofilia/
    6. Tomassy J, Khatri U, Perez L. HTA252 Analyzing Critical Dri- vers for Success in the Implementation of Outcome-Based Agreements to Manage Clinical Uncertainty Risks in Value Health. 2022;25(12):S345.
    7. Michelsen S, Nachi S, Van Dyck W, Simoens S, Huys I. Barriers and Opportunities for Implementation of Outcome-Based Spread Payments for High-Cost, One-Shot Curative Thera- Front Pharmacol [Internet]. 2020 [cited 2025 Jul 2];11. Available from: https://www.frontiersin.org/journals/ pharmacology/articles/10.3389/fphar.2020.594446/full


    EU PARLIAMENT TO EXTEND NEW MEDICINE DATA PROTECTION TO 7.5 YEARS

    The European Union is undergoing its most significant overhaul of pharmaceutical legislation in over two decades, a transformation that carries major implications
    for orphan drugs and rare diseases. On June 4, 2025, the Council of the European Union adopted its official position on what is known as the “pharma package”, a sweeping reform designed to modernize the existing regulatory framework of medicines in Europe.

    At the heart of the package is a revision of core legislation, including Regulation 726/2004, Directive 2001/83/ EC, and orphan and pediatric regulations (EC 141/2000
    and 1901/2006). The objectives are multi‑layered:

    • To ensure equitable and timely access to safe, effective, and affordable medicines across all EU member states.
    • To strengthen supply chain resilience, addressing medicine shortages.
    • To modernize regulatory processes to accommodate innovation.
    • To redesign incentives for orphan and pediatric medicines.

    Key elements of the Council’s position affecting rare diseases include the following:

    • Maintaining an eight‑year baseline of regulatory data protection, while proposing a reduced one‑year additional market exclusivity (down from the current two) for products that meet high unmet medical needs or reach broader market adoption.
    • The orphan drug exclusivity period remains at nine years but can be extended to eleven years if the product addresses significant clinical gaps.
    • Introducing a Member State right to require companies to supply sufficient product to meet national patient needs, a move aimed at preventing local shortages or uneven distribution.

    Importantly, the European Parliament had earlier endorsed amendments, such as a baseline of 7.5 years of data protection extendable under certain conditions, and retention of an explicit reference to orphan medicines within the PRIME scientific support scheme—
    but these were more ambitious and have since been modified in Council negotiations. Patient groups like EURORDIS have welcomed some elements while urging restoration of orphan‑specific support provisions to maintain momentum in addressing unmet needs.

    With the Council’s position now finalized, the trilogue negotiation phase between the European Parliament, Council, and European Commission is underway. The
    outcome of these negotiations in the coming months will determine the final legislative text to shape access and development of therapies for rare and paediatric diseases across the EU.

    This reform is arguably the most important legislative development in EU rare disease policy, because it extends beyond orphan‑specific rules and reconfigures the entire pharmaceutical environment to prioritize innovation, accessibility, equity, and sustainability.
    More information

    More information 

    EU EXPERT GROUP ESTABLISHED FOR PEDIATRIC AND RARE DISEASE DEVICES

    In July 2025, the European Commission published a regulation that establishes a new expert panel on medical devices focused on pediatrics and rare diseases. The measure was supported by many organizations and patient groups in the EU, who expressed hope that the panels would encourage the development of more devices to treat the pediatric population.The panel will provide scientific, technical, and clinical opinions to support the development of medical devices intended for small size patient populations, such as patients with a rare disease.

    The European Medicines Agency (EMA) currently has 11 expert panels that offer scientific and technical expertise for evaluating medical devices under the Medical Device Regulations and the In Vitro Diagnostic Medical Device Regulations. This new expert panel will become the twelfth.

    According to the EMA, the expert panels have several responsibilities: to provide their perspectives on the performance evaluation of high-risk in vitro diagnostic medical devices, to advise the Medical Device Coordination Group (MDCG) and the European Commission on the safety and effectiveness of medical devices and in vitro diagnostic medical devices, and encourage Member States, manufacturers, and notified bodies to consider various scientific
    and technical matters.

    MedTech Europe said it “welcomes the expansion of the expert panels’ scope to include a dedicated panel for paediatrics and rare diseases…. Overall this is a very welcome initiative, especially in light of the serious challenges posed by MDR and IVDR implementation, which have already contributed to the discontinuation of life-saving devices across multiple
    areas of healthcare, particularly in low-volume or high-need contexts such as paediatrics and rare diseases.”

    EURORDIS, a non-profit alliance of over 1,000 organisations representing rare disease patients, also voiced its approval of the initiative. “There is broad backing for the creation of a specialised panel focused on orphan and paediatric medical devices. At present, very few devices are designed specifically for rare diseases or children, yet they are vital tools for patients, their families, and healthcare providers dealing with complex and uncommon conditions.”
    More information

    NEW BLOOD TEST HELPS PHYSICIANS DIAGNOSE RARE GENETIC DISEASES IN INFANTS USING JUST A SMALL DROP OF BLOOD

     
    Researchers expect their test to reduce diagnostic time in clinical settings and help identify carriers of the diseases.Clinical laboratories have always been at the forefront of helping families battle rare  diseases. But such testing is sometimes invasive and expensive. Now there’s
    a new blood test that is minimally invasive and rapidly detects thousands of rare genetic diseases in infants and children using a mere 1ml of blood.

    Developed at the University of Melbourne and Murdoch Children’s Research Institute in Australia, the test rapidly detects abnormalities using proteomics to simultaneously
    analyze the pathogenicity of thousands of gene mutations that cause rare genetic illnesses.

    The single-drop blood test sequences of proteins present in the genes rather than the genes themselves to discover how genetic changes within those proteins affect function and lead to disease. According to the scientists, the test is cost-effective, potentially eradicating the need for other functional tests, and may be applicable to thousands of different diseases. Results of the test are typically available within three days, providing patients with earlier access to any available treatments.

    Getting the Right Diagnosis

    There are more than 7,000 types of categorized rare diseases which affect approximately 300 to 400 million people worldwide. These diseases are caused by genetic mutations that exist in more than 5,000 known genes. The new test focuses on rare genetic illnesses known as monogenetic disorders, such as cystic fibrosis and mitochondrial disease, that are caused by a single gene alteration or mutation.

    According to the National Organization for Rare Disorders, 25 to 30 million Americans are living with a rare disorder. A condition is categorized as rare if it affects less than 200,000 individuals.

    Global Genes states on its website that 400 million people worldwide suffer from a rare disease and half of those diagnosed are children. It also states that 80% of those diseases are genetic and 95% of rare diseases lack treatment approved by the US Food and Drug Administration.

    On average, it takes about five years to accurately diagnose a rare disease patient. During that period, that patient sees various specialists, undergoes difficult tests, and potentially faces the wrong diagnosis, Barr said.

    Initial results stemming from the new clinical laboratory test are encouraging, but more research and clinical trials are needed before the test can be used on a widespread level.

    More information

    WORLD HEALTH ORGANIZATION APPROVES RESOLUTION ON RARE DISEASES, SPONSORED BY SPAIN


    WORLD HEALTH ORGANIZATION APPROVES RESOLUTION ON RARE DISEASES, SPONSORED BY SPAIN

    The World Health Assembly of the World Health Organization (WHO) has given the green light to the resolution ‘Rare diseases: a global health priority for equity and inclusion’.

    The 78th World Health Assembly has adopted a landmark resolution declaring rare diseases a global public health priority, with the aim of promoting equity, inclusion and universal access to essential health services.

    The resolution, co-sponsored by Spain and Egypt, highlights the urgency of addressing the challenges faced by more than 300 million people living with rare diseases worldwide and their caregivers.

    According to the adopted text, WHO and Member States should work together to:

    • Develop a comprehensive global action plan (2025-2028): WHO will develop, in consultation with Member States and relevant organizations, a ten-year global strategic plan to improve diagnosis, treatment, research and comprehensive care for rare diseases. The draft will be presented to the 81st World Health Assembly in 2028.
    • Integration of rare diseases into national health systems: countries are urged to include these diseases in their public health policies, through national plans addressing prevention, early detection (such as neonatal screening), multidisciplinary care, rehabilitation and psychosocial support.
    • Strengthening universal health coverage: the resolution focuses on equity in access to essential services and calls on states to expand health coverage to ensure timely diagnostics, affordable medicines and health technologies, without placing a financial burden on families.
    • Promoting research and innovation: the need to increase public and private investment in research into rare diseases, many of which still lack effective treatment, is recognized. Partnerships between governments, scientific institutions, the private sector and patient organizations will be promoted.
    • Health education and training: the resolution emphasizes the training of health professionals from the formative stages, in order to improve detection, the clinical approach and provide appropriate care for patients, thus avoiding erroneous or late diagnoses.
    • Involvement of patients and civil organizations: the active inclusion of people living with rare diseases and their organizations in policymaking, health planning and service evaluation processes is encouraged to ensure a patient-centred approach.
    • Data collection and creation of national and international registries: countries are encouraged to create or strengthen rare disease registries, and to adopt coding systems such as ICD-11 or Orphaned nomenclature, to improve statistical visibility and evidence-based decision-making.
    • International cooperation and equitable access to treatment: cooperation between countries will be promoted to facilitate global access to effective, safe and affordable treatment, especially in regions with limited resources. The resolution also highlights the role of digital technologies, such as telemedicine, in bringing specialized care to remote areas.

    Furthermore, the resolution underlines the need to actively include patient organizations and people living with rare diseases in decision-making processes, as well as to remove the social, economic and cultural barriers that still today hinder their access to fundamental rights such as health, education and employment.

    The WHO will present an initial report on the implementation of this resolution in 2026, and a draft action plan in 2028, thus consolidating a new framework for global cooperation on these neglected diseases.

    More information 

    ELENA ARCEGA RABADAN – RESEARCH, VISIBILISATION AND INFORMATION: THE THREE PILLARS TO ADVANCE RARE DISEASES

    Elena Arcega Rabadan

    President of the Association for the Fight against Inflammatory Biliary Diseases (ALBI) Spain


    As a patient with primary biliary cholangitis (PBC) and president of ALBI Spain, could you tell us about your experience until you were diagnosed? What barriers did you encounter along the way, and do you consider that these difficulties are common in other countries with which you have contact through the association?

    EA: The truth is that my diagnosis process was not like that of most people. I was «lucky» enough to suffer a deep vein thrombosis, which led to more extensive tests. The changes were so obvious that the diagnosis came quickly. I was itchy and thought, «I must be allergic to bed sheets, who knows why». I felt tired, but I put it down to routine, to just «being tired». I had learned to live with it all without questioning it. It was only after the diagnosis, as I learned more about the disease, that I realised that I had had it for a long time without knowing it.

    In general, the problem with diagnosis in this disease is that it is often delayed. The tests may seem to be compatible with other things, and they say: «let’s see if it’s fatty liver» or «maybe it’s alcohol». Unfortunately, there are still doctors who, when faced with liver disorders, assume that there is high alcohol consumption. This bothers us patients deeply, because we feel that we are being judged without knowing our reality. But it is also understandable: the analyses can be confusing, and many professionals are not familiar with this disease, although fortunately it is becoming more widely known, even though it is still a minority disease.

    Another factor that greatly delays diagnosis is when the initial symptom, such as pruritus, brings you to the dermatologist. You start with one cream, then another, and so time goes by without anyone looking any further. This is not unique to Spain; it happens all over Europe. The time to diagnosis usually ranges from two to four years, as with many rare diseases. In my case, as I said, it was atypical. But the most important barrier we keep seeing is the same: lack of knowledge in primary care. It is understandable that they are not aware of all rare diseases, but it is essential that they suspect and refer early to a specialist.

    Fatigue, like pruritus, is a profoundly disabling symptom and continues to receive neither the attention nor the recognition it deserves

    PBC is a chronic, progressive and potentially disabling disease. How has it impacted on your quality of life and that of other patients with whom you have shared experience? What needs remain unmet today, both in clinical and social terms?

    EA: The disease has two main symptoms that particularly affect us: pruritus and fatigue. I start with pruritus because it is easier to explain. Itching is extremely unpleasant and can be disabling, especially at night. Yesterday I was talking to a patient who told me: «my day starts at two o’clock in the morning, when I can no longer sleep because I keep scratching». Added to this are poor sleep quality and the numerous problems that result from insufficient rest. Itching can even cause skin wounds. It is a symptom that, in my view, is not as highly valued as it should be, despite the enormous impact it has on quality of life.

    However, it seems that new treatments could offer better results, and we are hopeful that this will move forward and we will finally get this symptom under control. Then there is fatigue, which in PBC has a very particular nature. It’s as if you suddenly run out of strength. The day becomes shorter, because you do anything and you need to stop. Often, you know in advance that an activity is going to knock you out and that you’re going to need a day or two to recover. We have to learn to dose our energy. I often refer to the «spoon theory», popularised by a woman with rheumatoid arthritis: each action consumes a «spoon» of energy, and you have to work out how many you can spend per day.

    At first, you tend to normalise it. You think: «I’m tired, it must be because of what I’ve done». You don’t realise that fatigue is part of the clinical picture. It is surprising when you start talking to other people and they all tell you the same thing. Also, there is an important bias: most of the patients are women, mostly in middle age, many going through the menopause. And what we usually hear is: «you are tired like all women your age». But it’s not the same. You see that the people around you have an energy that you don’t have. They go out for dinner, for drinks, for socialising… and you just don’t make it. But, again, you end up normalising the symptom: «well, it’ll be my turn». And it shouldn’t be like that. Fatigue, like pruritus, is a profoundly disabling symptom and continues to receive neither the attention nor the recognition it deserves.

    In the context of rare diseases, access to innovative treatments is often unequal. Do you think that access to therapies for PBC varies significantly between countries? Have you identified notable differences in terms of funding, availability or drug approval times?

    EA: We experienced a complicated situation in this disease when a second-line treatment was negatively reassessed by the European Medicines Agency (EMA). This created a very difficult period for patients. In Spain, however, we were somewhat fortunate: patients who were already receiving this treatment were allowed to continue with it, as long as the doctor considered it to be beneficial. It was managed as a medicine for foreign use.

    In other countries, such as the United States and the United Kingdom, the same treatment continued to be prescribed as normal. In Europe, however, the decision was more drastic: it was completely withdrawn.

    After that, two new treatments arrived. One was approved in September and the other, if I remember correctly, in January. The truth is that sometimes my memory fails me (mental fatigue is also one of the symptoms of our disease) and I find it difficult to remember dates with precision. What is true is that, although the EMA approved both drugs, in Spain the process to final approval and pricing was slower.

    In our country, these two treatments were finally processed through an emergency procedure. Fortunately, they are now approved and available, but we have noticed that the process was more agile than in other cases precisely because we were coming from a critical situation: we had been left without a viable therapeutic alternative.

    The patient needs guarantees: to know that they will have access, that the treatment will continue, that it will work and that it will be monitored

    Talking to other rare disease associations, it is clear that there are important differences between countries in the timing of access to new treatments. And in many cases, these differences are very marked. In our case, the emergency pathway was fundamental in order not to leave patients without therapeutic options.

    From your point of view as a patient and association representative, what is your opinion on payment-by-results models that link reimbursement of a treatment to its real benefits for the patient? Do you think that such strategies can contribute to ensuring equitable and sustainable access to innovative therapies in rare diseases such as primary biliary cholangitis?

    EA: This is a very difficult question. I have given it a lot of thought and discussed it with doctors, pharmacists, hospital professionals and even with some pharmaceutical companies. While I have not had the opportunity to engage directly with Ministry officials, I have been able to converse with those close to the decision-makers. And yet, it is not an easy question to answer.

    I believe that payment-by-results models can facilitate the speedy introduction of medicines, and that is a very good thing. However, it can also have less beneficial effects if it is not well managed. For example, it could slow down the process on the part of the payer or the regulatory committee, because you get into a logic of «I give you the treatment now and we’ll see if we’ll pay for it later». This could lead to inequalities: not all patients may have the same access if pharmacies or hospitals decide to distribute treatments cautiously. In the case of minority diseases, as there are few patients, this should not represent a major problem for the sustainability of the system. But, I insist, it is not a simple matter. After much thought, I come to the conclusion that yes, it can be a positive model, as long as the patient is not directly affected and does not perceive it directly. It is something that needs to be managed between the Ministry and the pharmacies or funders, without interfering with the patient’s experience. The most important thing is that patients have access to the treatment. The patient needs guarantees: to know that they will have access, that the treatment will continue, that it will work and that it will be monitored by their doctor. This security is fundamental.

    The application of technological solutions in patient monitoring and real-life data collection is key to these models. What do you think is the role of patients in the generation and use of this data? Are there any international experiences that we should learn from to better integrate the patient’s voice in this process?

    EA: From my experience as a patient and also from what I see in my association, I think that rare disease patients are very eager to participate in clinical trials. But, paradoxically, those who are the worst off are often the ones who want to participate the most, and they are often precisely those who are unable to do so. If you’re well, you don’t take the risk; if you’re bad, you’re out of the trial. It’s a serious problem.

    And there is another drawback: the small size of the trials. Since these are rare diseases, the sample sizes (the n-values) tend to be very small. This makes the robustness and validity of the results very difficult. With so few participants and so few sites, it is not possible to do robust clinical trials. This is why I believe that more attention needs to be paid to real-life data.

    Europe is starting to move in that direction. Projects are being developed to put more value on studies based on real-life data. And I think this should be applied to practically all rare diseases: to include more quality of life tests, more tools that assess how the patient feels and how he or she lives in everyday life. For example, I cannot interpret my liver tests, but I can know if my tiredness is normal or not. And that part, which is essential, is what we should teach patients to communicate.

    How can we act? Just this morning a patient was telling me that her doctor was not paying attention to her when she talked about her fatigue. She said: «I’m exhausted, I can’t work and I can’t go to the gym.

    One of the two things I have to sacrifice». And her work is sedentary. But of course, the only thing they recommend is «exercise». As if that were so easy. She needs to move, yes, because it helps to improve her symptoms. But she also needs her doctor to understand that she can’t do everything. I suggested something that I think works for everyone: keep a calendar where you write down, by hours, what you do for two or three days. When you go to the doctor’s office, show it to him: «This is what I do, this is what I rest, this is what I sleep, this is my real life». It’s a way of showing fatigue in an objective way.

    There is a doctor I admire very much who recommends that, before every consultation, we print out a diagram of the human body and mark on it what has hurt us, when, how… if we have had a headache, joint pain, intense fatigue. Even if the liver doesn’t hurt (which it doesn’t), it helps us to situate and reflect on how we are doing. Going to the consultation prepared is key.

    I think we lack education as patients. We lack training to be able to communicate better how we feel. If we all prepared ourselves well before seeing the doctor (who already has very little time to see us), we could help him or her a lot. And the doctor would also be able to assess how we really are.

    It is important to be able to collaborate, get to know each other and work together for a common cause: the defence of patients, at a global level

    How does ALBI Spain work with other European or international organisations to support patients with inflammatory liver diseases? What opportunities exist to strengthen global collaboration in research, diagnosis and access to orphan treatments?

    EA: ALBI Spain collaborates with different international organisations. For example, we work with the PBC Foundation, participating in working groups within the European network ERN RARE-LIVER. We also collaborate with patient associations in the United States, especially in the field of advocacy and in the translation of content into Spanish to facilitate its dissemination in Spanish-speaking countries. We highly value the potential of language as a tool for cohesion and access.

    We are part of the Spanish Federation for Rare Diseases (FEDER), together with the National Federation of Liver Patients and Transplant Recipients (FNETH), and we also actively participate in ELPA (European Liver Patients’ Association). In addition, we are involved in the creation of a new European federation of associations focusing on rare liver diseases, which is taking its first steps this summer. Although I don’t remember their exact acronym now, we have already started working with them.

    In terms of treatment development and patient advocacy, we also collaborate with the pharmaceutical industry. We want to be informed about how the processes are progressing and to be able to bring in the patient perspective from the beginning. At the European level, we are in contact with associations in Portugal and Italy. There is a very positive relationship between organisations, and we are always willing to support each other in any way we can.

    I believe that ALBI Spain is positioning itself very well at the European level, and this will open many doors for us in the future. But beyond that, the important thing is to be able to collaborate, get to know each other and work together for a common cause: the defence of patients, at a global level.

    Of course, there are differences between countries. The UK, for example, has a very strong federation for diseases such as primary biliary cholangitis. We continue to work closely with them, although their situation is different because they are outside the European Union. They still use the second-line treatment that is no longer available here. As you can see, there are nuances and inequalities, but within Europe we are increasingly united. And that is great news.

    Our aim is to work for the diseases we support, and we do that as best we can

    Finally, what challenges do you see as priorities in the short and medium term in addressing this and other rare liver diseases, especially in relation to therapeutic innovation and access models that ensure equity at a global level?

    EA: The first thing we need is clear, accessible and up-to-date information. And second (but not least), research. We cannot stop research. In the minority diseases that we at ALBI support, there are many that are barely known, or that have not progressed for decades. And this cannot continue.

    We also need visibility. Doctors must play an active role in helping us to make these diseases visible and to accompany people who, for a long time, have felt alone. Knowing that there are more people like you is comforting and empowering. That is why we must continue to research and raise awareness, again and again.

    There are diseases such as autoimmune hepatitis that have been treated with the same drugs for more than 30 years. What if there was something better? We have to keep looking. Also in primary sclerosing cholangitis, a disease that often leads directly to transplantation. We know how to do transplants, but shouldn’t we consider how to avoid them in the first place?

    Progressive familial hepatic cholangitis is a very tough paediatric disease, although adults are also diagnosed. Caroli syndrome, for example, has only four or five people diagnosed in Spain. We need people to talk about it, for all hepatologists to know that it exists, and if they know of a case, they can share their experiences. The same happens with Alagille syndrome, which is also a childhood disease and which, although it can be treated, in many cases leads to a transplant. These are genetic diseases, many of them ultra-rare, which are still being researched little by little, and which need to be named. Because if they are not named, they do not exist.

    As an association, our role is to raise awareness, support patients, and dedicate all the resources at our disposal to this cause. We collaborate with whoever wants to collaborate, and we give everything we can. But we must not forget that we are volunteers… and we are also patients. And that is hard. Because, in addition to the work, we also carry our own itch, our own fatigue, our own «I can’t take it anymore» days. Most PBC patients suffer from fatigue or itching. It is true that some patients do not develop these symptoms and I wish we were all equally well. But many patients have no cure and continue to deal with chronic symptoms every day. That is why it is so important to strengthen research and visibility. We are linked to FEDER and EURORDIS, and we are also part of Orphanet. Our aim is to work for the diseases we support, and we do that as best we can.

    TAMARA HUSSONG MILAGRE- REDEFINING ACCESS AND EQUITY: THE VOICE OF EVITA IN HEREDITARY CANCER CARE

    Tamara Hussong Milagre

    Member of Associação de Apoio a Portadores de Alterações nos Genes Relacionados com o Cancro Hereditário (EVITA Cancro) – Hereditary Cancer, Association of Patients with Hereditary Oncological Diseases (Portugal)


    Could you briefly introduce the mission and work of EVITA Cancro in relation to patients with hereditary oncological diseases?TH: The EVITA Association for Hereditary Cancer supports patients and their families affected by hereditary cancer syndromes, focusing on advocacy, education, precision prevention, precision early detection, and access to precision medicine. Our mission is to empower patients and their families by providing information about genetic predispositions to cancer, facilitating early detection, and promoting access to appropriate treatments. We work to raise awareness about the unique challenges these patients face and advocate for their needs within the healthcare system.Currently, only 20% of genetic variant carriers with a high risk for hereditary cancer have been identified. The main barrier to genetic testing is the lack of genetic literacy among healthcare professionals outside oncology and medical genetics. Additionally, we face extremely long waiting times for genetic counseling, genetic testing, and the communication of results. To address these and other gaps, we have developed a digital platform called the EVITA Platform, designed to help individuals and healthcare providers assess cancer risks and determine if genetic counseling is beneficial. The platform includes a questionnaire based on national recommendations, provides immediate results and recommendations, and offers the possibility to schedule an appointment with our genetic counselor through a digital agenda. I can elaborate further on the platform’s multiple functionalities later if needed.

    Outcome-based payment models offer a promising strategy to improve access to therapies for rare or genetically based diseases, including hereditary cancer. 


    Based on your experience with EVITA and as a patient advocate, what are the main barriers to accessing innovative treatments, such as orphan drugs, in Portugal and across Europe?TH: Based on my experience within EVITA and as a patient advocate, several key barriers impact access to innovative treatments, including orphan drugs, in Portugal and across Europe. Regulatory hurdles and lengthy approval processes can delay access to new therapies, with considerable variability in regulations between countries adding further complexity. High prices for innovative treatments often pose challenges in securing reimbursement from public health systems, significantly limiting patient access. Additionally, there is limited awareness among healthcare providers, who may not be fully informed about available innovative therapies, leading to under-prescription and delayed treatment. Geographic disparities, differences in healthcare infrastructure, and varying levels of funding across regions also contribute to unequal access to treatments.
    How do you assess outcome-based payment models as a strategy to improve access to therapies for rare or genetically based diseases, such as hereditary cancer?TH: Outcome-based payment models offer a promising strategy to improve access to therapies for rare or genetically based diseases, including hereditary cancer. By aligning payments with patient outcomes, these models incentivize healthcare providers and pharmaceutical companies to focus on delivering effective treatments. However, their success hinges on accurately defining and measuring relevant health outcomes that truly reflect patients’ experiences and needs.
    One of the main challenges of these models is defining and measuring health outcomes that truly matter to patients. What role do you think patient organizations should play in this process?TH: Patient organizations play a critical role in defining and measuring health outcomes that matter to patients. They can gather direct patient input through tools like the EVITA Platform, which allows for periodic feedback collection. Patient organizations can facilitate discussions and collect patient feedback to identify what outcomes are most important. Promoting standardization by advocating for standardized metrics that reflect patient priorities in clinical trials and evaluations is essential. Collaboration with stakeholders (including healthcare providers, researchers, and policymakers) is also crucial, as patient organizations uniquely connect all these stakeholders, ensuring that patient perspectives are integrated into outcome measurement frameworks.

    There are several risks associated with outcome-based models, including potential delays in access

    Digitalization and the use of real-world data are becoming increasingly important in monitoring treatment outcomes. Are patients sufficiently informed and empowered to actively participate in such models?TH: While digitalisation and the use of real world data are advancing, patients often face challenges in being sufficiently informed and empowered to participate actively. Once again, our EVITA platform can help to ensure that patients are educated about these models and that their significance is crucial. We can help by providing resources and training on how to engage with digital tools and understand the implications of real world data actually. We have the EVITA school in mind to boost education and in multiple areas linked to the health literacy.
    In your view, are there any risks associated with outcome-based models, such as delays in access or lack of transparency in defining outcome indicators?TH: There are several risks associated with outcome-based models, including potential delays in access if payers and providers overly focus on specific outcome indicators. A lack of transparency in defining these indicators can lead to confusion among patients and healthcare providers regarding what constitutes success. Furthermore, these models may inadvertently prioritize short-term outcomes over long-term health benefits, potentially failing to fully capture the patient experience.
    Finally, from a European perspective, what best practices would you highlight regarding patient involvement in the evaluation and financing of innovative therapies? What recommendations would you make to policymakers to ensure that these strategies remain patient-centered?TH: From a European perspective, best practices regarding patient involvement include establishing clear policies that mandate patient participation in the evaluation and financing processes of innovative therapies. Supporting education initiatives is crucial, there must be investment in educational programs that empower patients to engage meaningfully in healthcare decisions. Creating collaborative platforms is also important to foster cooperation between patient organizations, healthcare providers, and industry in sharing insights and best practices.Our recommendations to policymakers include ensuring inclusivity by developing strategies that actively involve diverse patient populations in discussions about innovative therapies. It is also important to monitor and evaluate outcomes by implementing systems that assess the impact of patient involvement on therapy access and health outcomes. Lastly, legislative support is vital, there should be advocacy for legal frameworks that prioritize patients’ rights and access to innovative treatments. By prioritizing these best practices and recommendations, we can create a more patient-centered approach to healthcare that improves access to innovative therapies, particularly for those with hereditary cancer and other complex or rare diseases.

    ANNALISA SCOPINARO – INNOVATION AND EQUITY IN RARE DISEASES: UNIAMO’S VISION

    Annalisa Scopinaro

    President of the Italian Federation of Rare Disease Patient Associations (UNIAMO)


    UNIAMO is the Italian Federation of Rare Disease Patient Associations and plays a key role both nationally and internationally. Could you briefly explain UNIAMO’s mission and how the organization works to improve access to diagnosis, treatments, and innovation for people living with rare diseases in Italy?

    AS: UNIAMO’s mission can be summed up in one sentence: to improve the quality of life for people with rare diseases. Of course, this is easier said than done. Achieving this goal requires the implementation of a variety of actions involving multiple stakeholders within the complex rare disease ecosystem.

    All of the Federation’s activities follow a defined strategy, which is structured around four key pillars in the field of rare diseases: early diagnosis, holistic care, research in its various forms, and the development of new therapies, particularly for diseases that are still without treatment options. These represent the Federation’s four macro objectives. In terms of access to diagnosis, treatment, and innovation, it is essential to serve as a bridge between patient associations and institutions.

    For example, in Italy, thanks in part to the commitment and efforts of patient associations and to UNIAMO’s institutional advocacy, the law on Expanded Neonatal Screening (SNE) was approved in 2016. This program ensures early diagnosis and care for all newborns, identifying more than 40 rare metabolic disorders at birth. Since then, the SNE panel has been updated to include additional diseases for which effective therapies have been developed and will continue to evolve in the future through technological innovation.

    The role of the Federation, not only in the area of diagnosis but also in therapies and care pathways, is to identify and respond to the needs of people with rare diseases and to bring those needs to the attention of institutions and policymakers. The goal is to ensure that the system becomes increasingly capable of embracing innovation and making it accessible to those who need it.

    From UNIAMO’s perspective, how do you assess the potential impact of outcome-based payment models on access to innovative therapies for patients with rare diseases?

    AS: While waiting for European legislation to allocate costs based on the multi-year benefits of therapies, the Italian Medicines Agency (AIFA) has, in recent years, experimented with various payment models to ensure the sustainability of the healthcare system, even in light of the uncertainty surrounding the long-term effects of certain therapies.

    Italy has stipulated reimbursement agreements based on patient response, the so-called ‘payment at results’

    On one hand, there is a clear need to be able to spread financial risk over multiple years. On the other hand, it is equally important to allow for the early introduction of some therapies across several countries. If the full cost of a treatment is accounted for in a single year, many countries may be discouraged from approving the drug, despite its long-term benefits.

    Are there any examples or experiences you would highlight from Italy or from the European Reference Networks (ERNs) regarding the implementation of outcome-based payment models or models based on real-world outcomes?

    AS: The uncertainty regarding the long-term benefits of these drugs has pushed Italy to stipulate reimbursement agreements based on patient response, the so-called «payment at results». This is one of the forms of deferred payment: if the drug does not have the expected effects, the company reimburses the buyer via credit note. I would like to point out that among the various types of payment there is also «payment by result», currently used for CAR-Ts.

    Another formula used is that of the budget cap based on two indicators: number of patients and negotiated price (the objective of the budget is prescriptive appropriateness and management of pharmaceutical spending) at the contractual expiry of 12/24 months, AIFA verifies compliance with the negotiation condition and in case of excess spending the pharmaceutical company will have to pay a payback to the NHS.

    In practice, what are the main challenges you see in implementing these models from the patient’s perspective? Are there concerns related to equity, transparency, or delays in access?

    AS: Patients are generally not directly affected by how regulatory authorities decide to reimburse a treatment. What does impact them, however, is when a country chooses not to approve a treatment due to its cost. This is already creating significant equity issues. For example, we know that Italy ranks second in Europe for the number of drugs approved (although the average approval time is 437 days), but many other countries do not approve all available treatments. In some cases, it is the pharmaceutical companies themselves that choose not to enter into price negotiations because the expected number of patients in a particular country does not justify the time and cost required to negotiate with regulatory authorities.

    For people living with a rare disease, it is essential that once treatments are authorized, they are made available as quickly as possible, especially in two critical situations. The first is for diseases that currently have no available treatment, and the second is for highly degenerative conditions for which no effective therapies exist to slow disease progression. For these two categories in particular, the concern shared by the entire community is that access to treatment should not be delayed due to bureaucratic processes related to national price negotiations.

    Technological innovation is improving the track health outcomes. Do you believe the European healthcare system is prepared to effectively support these models? What technological or structural barriers still remain?

    AS: What we hope for at the European level, together with Eurordis and, consequently, UNIAMO, is the development and adoption of models that, in certain cases involving ultra-rare diseases, can centralize reimbursement at the European level. This would help prevent access issues, especially when therapies are available only in a limited number of highly specialized centers across Europe. Access in these situations is far from straightforward: while cross-border healthcare exists, its practical implementation is neither simple nor guaranteed. Furthermore, when a treatment is not approved, it cannot be reimbursed, even under cross-border care schemes. Challenges persist, and there is a clear need at the European level to establish a different model of approval and distribution for certain ultra-rare disease treatments. This is no small task, given that healthcare systems remain under national jurisdiction, and in the case of Italy, even regional.Nevertheless, the issues
    are beginning to surface more clearly, and a broader recognition of the need for change is gradually emerging

    It is essential to assess not only the clinical effects of a treatment, but also its impact on quality of life

    From the point of view of patients and their associations, how can we ensure that innovative financing models always prioritize clinical benefit and patient quality of life over economic interests?

    AS: UNIAMO took part in the consultation launched by AIFA regarding the new criteria used to determine the innovativeness of a drug, criteria that, in Italy, grant access to a dedicated reimbursement fund and a fast track for availability. Our comments focused on the importance of including Patient-Reported Outcomes (PROs) and Patient-Reported Experiences (PREs) among the evaluation criteria. It is essential to assess not only the clinical effects of a treatment, but also its impact on quality of life. Innovative financing models should, to some extent, begin to take these broader aspects into consideration as well.

    UNIAMO is actively involved in dialogue with regulatory authorities, the pharmaceutical industry, and healthcare professionals. What role do you believe patient organizations should play in the design and implementation of outcome-based payment strategies?

    AS: While maintaining the perspective that patients’ primary interest is to access treatments as quickly as possible, UNIAMO is also firmly convinced that it should not be patients or patient representatives who take part in discussions about drug pricing. The discussion around the price of a treatment involves a number of complex factors that must be assessed by experts in pharmacoeconomics, health economics, and related fields. The role of the patient representative is crucial in clearly expressing the value and benefit that a given treatment brings to the patient, but they should not be involved in the pricing negotiations themselves.

    According to you, which of the good practices developed in Italy could be used internationally to improve patient access to orphan drugs?

    AS: In Italy, a great deal of work has been done to ensure early access to all available treatments; in fact, we rank second in Europe for the availability of orphan drugs. This achievement has been made possible thanks to a regulatory framework that has been developed over the years. One example is Law 648 of 1996, which allows for the use of drugs that are not yet authorized in Italy but can still be reimbursed by the National Health Service (SSN). This law permits access to drugs that are either in clinical trials or already approved in other countries, subject to AIFA’s authorization, when there is no valid therapeutic alternative available for serious, rare, or life-threatening conditions.

    Additionally, Law 326 of 2003 established a National Fund within AIFA to support the use of orphan drugs for the treatment of rare diseases, as well as drugs that represent a potential therapeutic hope, pending commercialization, for specific and serious conditions. These examples of regulatory measures that enable early access could also serve as useful models to be adopted or adapted by other countries.

    CARLOS MARTÍN SABORIDO – BEYOND CLINICAL BENEFIT: ADVANCING VALUE-BASED FINANCING FOR RARE DISEASES

    Carlos Martín Saborido

    Director of the Health Technology Assessment Agency at the Instituto de Salud Carlos III, Spain


    From your experience in institutions such as NICE in the United Kingdom and the European Commission, how do you assess the current state of outcome-based payment strategies applied to orphan drugs in Europe?

    CMS: In the UE, some countries are using the same tools for orphan drugs as for common drugs, to address both clinical and financial uncertainty. However, some Member States are focusing only on financial uncertainty. So, I think there is no unified or standardized approach to assessing orphan drugs across Europe.

    So far, I think that the situation remains very variable. You mentioned NICE, which indeed has a very clear position on how to address orphan drugs. They clearly distinguish between clinical and financial uncertainties, for example, using the Innovative Medicines Fund.

    Still, I’m very optimistic. In the next three to four years, when the Joint Clinical Assessments (JCAs) are more widely integrated into national systems, we may start to see some common trends in the way orphan drugs are assessed across Europe.

    Which European countries would you highlight for successfully implementing outcome-based financing models for medicines targeting rare diseases? What best practices could be transferred to other healthcare systems?

    CMS: It’s somehow complicated to say what constitutes a successful implementation of these outcome-based financing models, mainly because some Member States do not share enough information to properly evaluate how the agreements have actually worked. As a result, it’s difficult to assess the success of these models in practice.

    However, we can comment on their implementation, how these models are being put into place, even if we don’t yet know how effective they are. In this regard, Italy is worth highlighting, due to the regional registries they have established, and Finland as well, thanks to the real-world evidence systems integrated into their hospitals. Both countries are very focused on gathering insights and generating evidence from real-world data to assess how these outcome-based financing models are functioning.

    We are moving in the right direction, but we still need much more trust and cooperation between Member States

    It’s also important to clarify that your question refers specifically to rare diseases, not necessarily to orphan drugs. Outcome-based financing models applied to medicines used in rare diseases are not always applied to orphan drugs. This distinction matters, as certain orphan drugs lose their orphan designation over time when they start targeting larger patient populations. So, in some cases, these outcome-based financing models are not directly addressing rare diseases per se, but rather orphan drugs which may be used for rare diseases or for low-prevalence conditions.

    Digitalization and interoperability of health data are key to measuring real-world health outcomes. Is Europe technologically and regulatorily prepared to widely implement outcome-based payment models?

    CMS: I would say this is not happening widely across the European Union as a whole, although some Member States are indeed very advanced in this regard. The main limitation probably comes from the lack of data sharing. To successfully implement outcome-based payment models, we need not only strong data digitalization but also widespread access to that data.

    I’d also like to mention the European Health Data Space. With its vision and the potential for secondary use of health data to support outcome-based agreements, I think we are moving in the right direction. That said, and to be fair, we still need much more trust and cooperation between Member States.

    Within the framework of the new European regulation on joint health technology assessment (HTA), how do you think the incorporation of these innovative payment models could be harmonized among European countries?

    CMS: It’s a complex question, especially since you’re referring to joint health technology assessment, so you may be alluding specifically to the JCAs under the new regulation. The main expectation from this regulation is to establish a common synthesis of clinical evidence. What we aim to achieve with the new HTA regulation is the definition of shared outcomes that can be measured and included into innovative payment models.

    I think this is something that needs to be emphasized in the coming months: we need to acknowledge that the Joint Clinical Assessment (JCA) will define a set of outcomes that are relevant at the European level. These are the outcomes that should serve as the basis for innovative payment models. This is the only way to ensure that the data generated is comparable and usable across Member States, and this is essential for harmonizing outcome-based models across European countries.

    We need to recognize that both the number and type of outcomes required should be driven by the Joint Clinical Assessment. Otherwise, each Member State may select different outcomes for their innovative payment models, which would hinder alignment and comparability across the EU.

    From an international perspective, what structural or methodological barriers still persist for the adoption of value-based models in the field of orphan and advanced therapies?

    CMS: This question overlaps with the topic of advanced therapies, so I’ll try to address it more broadly, although I believe we’re actually discussing distinct but related issues.

    The first challenge is the definition of value, what exactly do we mean by it? Value is not limited to clinical benefit; it’s not just about efficacy or safety outcomes. Many other factors come into play when assessing value. So, I would say the first methodological barrier is precisely the lack of a common, agreed-upon definition of value. The second barrier is the ability to collect data that reflects that value. We need a clear and consistent methodology for capturing such data.

    One critical aspect of defining value is understanding the real burden of rare diseases and the impact that new technologies have on that burden. This is extremely challenging. In Spain, for instance, we’re working on a project called Argos, which aims to collect data on the resources patients use to live with a rare disease. I believe this kind of information is essential for accurately defining value.

    If we are able to gather the right data, define value properly, and share information efficiently, we can move forward

    In addition, there’s also a structural barrier related to data collection: the lack of a shared data collection system and coordinated infrastructure. For some orphan drugs and rare conditions, the European Reference Networks are already collecting and sharing common datasets. This is a valuable model that could be replicated in the context of pricing and reimbursement. Moreover, we should aim to collect relevant data directly from patients, not only from clinicians, as this remains a limitation in many cases.

    If we are able to gather the right data, define value properly, and share information efficiently, we can move toward robust value-based and outcome-based agreements.

    How can it be ensured that these financing models always prioritize clinical benefit and equity in access over other interests, especially in rare diseases where evidence is more limited?

    CMS: This is a serious misconception, the idea that we should prioritize clinical benefits above all else. Of course, we need to set priorities, but they should not be based solely on clinical outcomes. In fact, in the previous two questions we’ve already discussed the broader concept of value. I believe that focusing exclusively on clinical benefit is a trap. If we prioritize only clinical outcomes, we risk overlooking treatments that truly deliver meaningful value.

    Take, for example, a new drug or technology that may offer only modest clinical benefits, but significantly improves the lives of caregivers by simplifying care or easing daily routines. That treatment should be reimbursed, not just because of its clinical efficacy, but because of the overall value it brings to patients and their support networks.

    When we talk about rare diseases, it’s rarely just about clinical benefit. It’s also about how a technology improves the quality of life for informal caregivers, parents, and others who support the person living with the condition. So I apologize if my position seems disruptive, but I firmly believe that clinical benefit alone should not be our sole priority. We must prioritize value, and, equally important, equity.

    We must adopt a holistic view, considering not just clinical benefits, but the broader value a new therapy or technology brings

    Looking ahead, what opportunities do you identify to strengthen European cooperation around assessment, reimbursement, and outcome-based financing of orphan drugs, with the goal of achieving more equitable and efficient access to innovation?

    CMS: You mention three main areas here, assessment, reimbursement, and outcome-based financing. I believe it’s essential to approach them step by step.

    The first priority must be collaboration to establish a shared value framework for assessment. Only once that foundation is in place can we meaningfully move forward with discussions on reimbursement and financial models. Without a common framework for value assessment, we risk creating inconsistencies across Member States, with some approving drugs based solely on clinical benefit, while others reject them due to differing interpretations of that benefit. That’s why defining a shared value framework is not only the first step, but the most critical one.

    Regarding outcome-based financing in the context of orphan drugs, it’s important to recognize that it may not always be the right solution. What we truly need is innovation in financing, and that doesn’t necessarily mean outcome-based models.

    Returning to the earlier point on clinical outcomes: if we rely exclusively on outcome-based agreements and focus only on measurable clinical results, we may end up tracking outcomes that provide little or no real clinical benefit. In many cases, what we need is a value-based financing model, not merely an outcome-based one.

    Sometimes, value-based systems will include outcomes, particularly when the value lies in clinical efficacy or effectiveness. But other times, the value may lie elsewhere. Therefore, we must adopt a holistic view of patients with rare diseases, considering not just clinical benefits, but the broader value a new therapy or technology brings. This is why collaboration is key: only by working together can we build a robust and consistent value framework for assessment. Only then can we move forward with reimbursement models and value-based agreements.

    So, when it comes to rare diseases, we likely need to shift toward financing systems that are value-based, not purely clinical or outcome-driven. Otherwise, we risk missing a substantial part of the value these new technologies offer.

    MANEL FONTANET SACRISTÁN – PAYMENT BY RESULTS AND REAL-LIFE DATA: TOOLS FOR A SUSTAINABLE SYSTEM

    Manel Fontanet Sacristán

    Medicine Access Coordinator. Rational Use of Medicines Division. Medicines Department. Catalan Health Service. Government of Catalonia


    From your experience at CatSalut, how would you describe the evolution of payment by results models applied to orphan drugs in recent years? What differences do you observe with respect to other European countries?

    MF: At CatSalut, the application of managed access models has always been a clear line of work, not only in the field of orphan drugs. In fact, we have published a guide with recommendations and areas of application. Therefore, in general terms, it is already a priority area for development within the framework of incorporating innovation in the Catalan health system.

    In the particular case of orphan drugs, two relevant circumstances converge. On the one hand, due to the idiosyncrasy of rare diseases and their low prevalence, the evidence generated often does not reach the ideal level that we would like to have. This, of course, can be improved, but it can hardly match the evidence we obtain under more frequent conditions.

    On the other hand, the small size of the market means that the cost of these drugs is, in general, very high. These two circumstances, therapeutic uncertainty and financial uncertainty, make orphan drugs particularly suitable for the application of management measures in their incorporation into health systems, such as payment-by-results models.

    From our perspective, we are pleased to note that in recent years there has been a progressive increase in the number of medicines financed through these access models, which makes it possible to better align the price of drugs with their therapeutic value and, at the same time, to better manage the economic resources allocated to them.

    It is important to bear in mind that, since the adoption of the European regulation in 2000, the number of authorised orphan drugs has exceeded 250. We are pleased to see how these access tools have been progressively implemented and have facilitated the incorporation of innovation in health systems.

    With regard to comparison with other environments, especially in Europe, there are differences. There is no single reference model in Europe. This is partly due to the confidentiality of funding processes in each Member State, which limits access to comparative information. But it is also true that there are divergent positions: while some countries, such as Italy, have historically favored payment-by-results models, others have adopted strategies that place less emphasis on this approach.

    These methodologies favour the rapid, effective and sustainable incorporation of medicines into health systems

    In our view, the key issue is to identify the uncertainties (both therapeutic and financial) and to try to address them through models that allow them to be managed. We must also take
    into account a key aspect that explains many of the differences in the application of these models in Europe: transaction costs. These models require a significant implementation effort, with a consider- able workload, and this partly explains the differences in their deployment and diffusion in different countries.

    Outcome-based agreements seek to link the price of therapies to their actual clinical effectiveness. From your perspective, what are the main opportunities and challenges posed by their application in the field of rare diseases?

    MF: The main opportunity, in my view, is that these models enable the cost of a therapy or intervention (such as a drug) to be directly linked to the price paid by the health system. This represents a direct tool for managing uncertainty. The more certainty a system has about the decision it needs to make, the more quickly and comfortably it can make that decision.

    These are therefore methodologies that favour the rapid, effective and sustainable incorporation of medicines into health systems. In that sense, I think they is a great opportunity.

    Moreover, these models generate some positive externalities that, although they are not the main reason for their implementation, they do contribute to building a health system oriented towards the continuous collection of health outcomes through- out the life cycle of the medicine. In other words, beyond the direct benefits of the model itself, there are additional effects that help to consolidate a system focused on measuring outcomes, whether drug treatments or other interventions.

    However, the challenges involved are also significant. We are talking about an environment of uncer- tainty, with limited knowledge compared to what happens in more prevalent diseases. Therefore, defining a payment-by-results scheme is not always straight- forward. It is necessary to establish variables that clearly delimit what is considered a «response» to treatment, to do so in a clinically meaningful way, and also to define reasonable time horizons for both parties: both for the funder and for the pharmaceutical company. And this, I insist, is not easy.

    On the other hand, information systems, while functional in many cases, often exhibit limitations or areas for improvement in the collection of real-world data. These challenges stem less from technical deficiencies and more from the substantial effort demanded of the professionals tasked with managing and populating these systems

    These systems must collect the health outcomes that then allow the assessment of compliance with payment-by-results agreements. And all this work entails significant transaction costs, both for healthcare professionals and for the administration and the pharmaceutical companies themselves.

    In our environment, we view these models favourably, but we also recognise their challenges: from agreeing on a clinically valid and measurable response criterion in the appropriate time frame, to having sufficiently sensitive information systems to capture the results. All this, without forgetting the operational burden for all actors involved in the implementation of these schemes.

    Internationally, there is growing interest in integrating real-world data into these funding models. What role do you think real- world evidence should play in making these arrangements more effective and reliable?

    MF: Real-world data is undoubtedly one of the priority areas to develop, especially in those contexts where, due to the rarity of diseases, it is not always possible to generate evidence under the ideal standard of knowledge, such as clinical trials.

    Real-world data is undoubtedly one of the priority areas to develop, especially in those contexts where data are scarce

    I would distinguish two levels of application. Firstly, at the ex ante level, i.e. at the moment when the funding of a medicine is being assessed. At that point, I think it is essential to take into account all available evidence, including real world evidence. However, it is also important to weigh the weight and strength of that evidence against other sources which, from a methodological point of view, may be more robust, such as clinical trials themselves.

    Therefore, I agree that real-life evidence should be considered during the initial decision-making process, especially in settings where data are scarce and any additional information can be useful to make more informed decisions. But I insist: they must be properly assessed, giving them a weight proportional to their quality and methodological strength, which is probably lower than that of the available clinical trials.

    Secondly, at the ex post level, real-life data are also very relevant. One of the key orientations of the system should be the continuous review of previously made decisions. Therefore, having data generated after the drug has entered the system is essential for learning, generating new knowledge and adjusting the decisions taken, also with regard to funding conditions, not only to the clinical use of the drug.

    This requires, again, that we are able to assess the quality of the evidence we are generating, or are able to build, with the current information systems. And this is where another fundamental challenge comes in: to have systems that are sufficiently prepared to produce real world evidence of quality.

    We need that evidence to be robust enough to be of real use for decision-making. Ex post evaluation of the use of medicines should allow us to review, adapt and improve our funding decisions based on knowledge generated in real practice.

    What international experiences or best practices would you highlight as reference models in the implementation of payment by results strategies for orphan drugs?

    In terms of international strategies, although they do not strictly refer to the payment by results model, I do believe that there are prior stages that are necessary before applying any access measure. The first is to assess the therapeutic value of a medicine, i.e. to understand what its real clinical contribution is. From there, we can start to build the most appropriate financing system.

    In this respect, I believe that a very useful step for- ward will be the new European Regulation on Health Technology Assessment (HTA), which proposes a single joint clinical assessment at European level. This assessment will be more agile, agreed between the different countries and, therefore, can become a first key element in the construction of access and funding, even in cross-border contexts.

    As for other tools or international experiences that we value positively from the Catalan health system, perhaps there is no single reference model, but there are several interesting ideas. One of them is undoubtedly the link between the price of the medicine and its therapeutic value. The approach systematically applied by NICE (National Institute for Health and Care Excellence) in the United Kingdom, which introduces economic evaluation as a methodological basis for decision-making, seems to us to be very relevant. Through this analysis, a clear relationship is established between health outcomes and the costs associated with the intervention.

    There are also other interesting European experiences reported in the literature. For example, Italy has widely applied payment by results schemes.

    Another valuable experience, mentioned above, is that of the Netherlands. There, they work with the idea of adapting access conditions as new evidence is generated in real clinical practice.

    This approach makes it possible to adjust decisions on the funding of a medicine according to the data that are obtained in its daily use. This willingness to continuously adapt based on real world evidence seems to us to be particularly useful and perfectly applicable in our context as well.

    Digital technologies and integrated data systems are key tools for implementing and monitoring these models. Do you think that European healthcare systems are technologically prepared to support them? What barriers still exist?

    MF: I think the area of information systems is one of the biggest challenges facing health systems today. Are they ready to implement managed access models, such as payment by results schemes? I guess the answer is yes, because they are being applied, they are being implemented and, in many cases, successfully. Therefore, the formal conclusion should be that they are indeed ready.

    Including patients not just as observers, but as active participants, is a prerequisite for a fairer, more effective and responsive system

    However, it is also true that these information systems need improvements: advances in automation, in automatic data capture, in interoperability… All of this to reduce the workload that currently falls on health system professionals when these schemes are implemented.

    Payment by results models are already being used in our environment and in different European countries, but they entail a considerable operational effort. Therefore, transaction costs are relevant, and this poses a major barrier to scaling up these measures. We cannot apply these models to all medicines entering the system: there would simply not be the capacity, in terms of workload, to manage them all. So there is also a clear need for improvement of information systems, to reduce the effort required and facilitate the implementation of these models within the health system.

    The challenges are basically the same as those faced by all health systems: the need to capture adequate data, to ensure interoperability between different environments… And this is precisely what most systems are working on today.

    In addition, European regulations will also mark an important step forward. Initiatives such as the European Health Data Space and the general adaptation of information systems to these new requirements will be a key stimulus. All this will contribute to making these tools, which we are already applying, easier to implement, more scalable and extendable to a larger number of medicines.

    And this secondary use of data will undoubtedly also help us to generate much more knowledge, thanks to the pooling and integration of information from different environments.

    Collaboration between funders, industry, regulatory authorities and patient organisations is essential for the success of these innovative formulas. How could this collaboration be strengthened at the international level to ensure equitable access to orphan drugs?

    MF: I believe there are a number of areas where international collaboration could be strengthened, many of which are already under development and are likely to be enhanced in the coming years.

    One of them is the early dialogue between all the actors involved in the healthcare system. I think it is very interesting to generate early dialogues between regulators, funders, developers, patients and healthcare professionals. Spaces in which the expectations and needs of certain stakeholders can be anticipated, alongside the possibilities and constraints of others.

    This type of dialogue has already begun to be facilitated at the European level, for example, by the EMA, through initiatives such as the EUnetHTA network, among others. There is a certain degree of development of these spaces for early conversation,and they will surely be reinforced with the entry into force of the new European Joint Clinical Assessment regulation, which will contribute to the regulatory harmonisation that we so desperately need.

    Having a more harmonised, agile and predictable regulatory framework will undoubtedly facilitate the introduction of innovation in the system. This will allow us to better align the expectations of all takeholders and reduce uncertainties in key clinical and economic decisions.

    Another element that could also be very valuable is the development of more open models of innovation and discussion, with effective participation of all stakeholders and with spaces that allow ideas and approaches to be gathered from different perspectives.

    In fact, the European regulation itself envisages the possibility of establishing regulatory sandboxes in the field of orphan drugs. These regulatory tests can help us to be more agile and to find innovative responses to facilitate the incorporation of new treatments, especially in a field as complex and in need of solutions as rare diseases.

    Looking ahead, what do you think should be the key priorities at European and global level to ensure that payment by results models really contribute to a more sustainable and patient-centred ecosystem in the field of rare diseases?

    MF: I believe that there is no single measure, but rather a set of actions that should be leveraged in a complementary way, and that all of them together would contribute to improving access and strengthening the performance-based funding tools that medicines have within the system.

    One of the building blocks is the evaluation of medicines. This should be the first step before any funding decision is taken. In this sense, it is key to deepen the current evaluation models, both in the framework of the European regulation and, in the case of Spain, in the context of the future Royal Decree on Health Technology Assessment (HTA). Ensuring continuity and robustness in this assessment model is essential, particularly in the case of orphan drugs

    Another key aspect is to strengthen the current infra- structures of our information systems. This is essential to reduce the workload of professionals, facilitate data collection and better exploit the secondary use of the information generated. These data not only allow us to generate clinical or epidemiological knowledge; they are also essential to implement managed access models, such as payment by results schemes.

    In addition, it is necessary to establish mechanisms for periodic review of the decisions taken. Knowledge is not static: it evolves as medicines are used and rela-world data are generated. Therefore, being able to observe results and adjust decisions on an ongoing basis is an essential part of the process.

    And finally, regarding how to incorporate patient-centred innovation: the key is precisely to ask patients. Listen to their experience and integrate them into decision-making processes at all possible levels. Including patients not just as observers, but as active participants, is a prerequisite for moving towards a fairer, more effective and responsive system.

    NO TE PIERDAS